Hemisection of the spinal cord results in a contralateral loss of pain and thermal sensation due to spinothalamic damage, and ipsilateral loss of proprioception due to posterior column damage.
There is also an ipsilateral motor paralysis due to destruction of the corticospinal and rubrospinal tracts as well as motor neurons.
Complete transection of the spinal cord would cause a bilateral spastic paralysis, and there would be no conscious appreciation of any cutaneous or deep sensation in the area below the transection.
Posterior column syndrome would result in a bilateral loss of proprioception below the lesion, with relative preservation of pain and temperature sensation.
Syringomyelic syndrome results from a lesion of the central gray matter. Pain and temperature fibers that cross at the anterior commissure are affected, which may result in bilateral loss of these sensations over several dermatomes. However, tactile sensation is spared. The most common cause of this type of syndrome is syringomyelia. Trauma, hemorrhage, or tumors are other possible etiologies. If the lesion becomes large enough, then other spinal cord systems become affected as well.
Tabetic syndrome results from damage to proprioceptive and other dorsal root fibers. It is classically caused by syphilis. Symptoms include paresthesias, pain, and abnormalities of gait. Vibration sense is most affected.
Initially he had a bilateral spastic paraparesis and urinary urgency, but this has improved. He still has pain and thermal sensation loss on part of his left body and proprioception loss in his right foot. There is still a paralysis of the right lower extremity as well. The patient had Brown-Séquard (hemisection) syndrome .
Thursday, 7 January 2010

Wednesday, 23 December 2009
Pediatric Stridor - Notes
BMJ article notes.
Reference:
Majumdar S., et al. Pediatric Stridor. BMJ 2006; 91-4:101-105.
Notes:
Definition: High pitched noised due to turbulent airflow through a partially obstructed airway
Types of stridors:
- Obstruction at the level of the glottis or subglottis = inspiratory stridor
- Obstruction at the level of the supraglottis = stertor, low pitched sound
- Obstruction at the extrathoracic trachea = biphasic stridor
- Obstruction at the intrathoracic trachea = expiratory stridor.
Mechanism of stridor:
- Pediatric airway: epiglottis at level of atlas, cricoid cartilage at the level of C4.
- Apposition of the epiglottis and the soft palate= suckling and nasal breathing
- Thyroid cartilage is partly contained causing the laryngeal skeleton to be compact.
- With age, larynx grows, epiglottis increases faster than the rest of the larynx.
- Sub-glottis = 4-5cms and rich in mucus glands.
- Aspiration and laryngospasm due to inefficient closing and opening laryngeal reflex.
- Trachea tends to collapse more readily due to increased negative intrathoracic pressure.
Important physical sign in management of the stridor:
- If the airway is flexible causes the wall to collapse due to the linear flow of air rather than the lateral.
- Airway resistance is inversely proportional to the fourth power of the radius, hence, if the radius decrease by 0.5 will cause a 16 times increase in resistance.
Diagnosis and Initial Management:
- H/o of time; mode of onset of stridor
- Pyrexia, hypoxia
- Respiratory distress
- Severity of stridor during sleeping, wakefulness
- Feeding behavior
Child can stop making stridor noises due to difficulty to move enough air to generate a sound or because there is a soft lesion like laryngeal papillomata à do not exclude diagnosis.
Radiographs: Metallic foreign bodies that narrow airway; Ultrasound: used to check masses or vocal cord function, Contrast swallow for trachea-esophageal fistula or laryngo-tracheal clefts.
MRI/CT: vascular abnormalities
Endoscopy and Laryngoscopy.
Conclusion:
Identify cause, secure airway, restore normal respiratory function. Thorough history required for diagnosis.No plagiarism was intended, just notes from the article. All credits to the author.
Friday, 9 October 2009
My first cast
I fell.
There were no fluroscent warning step lights, the lecture hall was dark but I went down to help the doctor to help her switch back on the lights and I tripped over a double stair. I got a grade 1 lateral ligament sprain with a little bone bruising.
Generally, no one gives a heed to small falls like these but an ortho prof. told me that I needed to go the hospital becuase of the bone pain.
'Look out for the Ottawa guidelines or something for pain'
The cast was placed and a 3 weeks heel period was given.
Friday, 18 September 2009
My first day at the hospital...
"... It was my first day as a medical student at our regional hospital. We reached earlier than our doctors technically doctor... one was already doing the end of the day meeting with the senior students. We're supposed to divide ourselves into groups and then go around witnessing the signs of sickness... and in some cases... defeat!..."
A small snippet of my already blogged post.
http://confused8589.blogspot.com/2009/09/first-time-was-not-at-all-easy.html
This is where the post was originally posted.
Thanks.
A small snippet of my already blogged post.
http://confused8589.blogspot.com/2009/09/first-time-was-not-at-all-easy.html
This is where the post was originally posted.
Thanks.
Friday, 19 June 2009
"What Makes Us Humans Unique" by Dr. Dov Michaeli
Disclaimer: This entry does not belong to me. Not a single word other than the disclaimer part. I do not own any of the rest. It's rightful owner is Dr. Dov Michaeli who posted it on Medscape, and to Dr. Ajith Varki whose work is being talked about, and I happened to receive this amazing piece and wanted to share it with people who haven't signed into Medscape yet.
What makes the human superior to the ox? So mused King Solomon, the wisest man in the 10th century BCE. Since then, this question has occupied the best minds of the human race, from Plato in the fifth century BC to modern-age molecular biologists, neurobiologists, neuropsychologists, and philosophers. Is it intelligence? Communication? Empathy? It is now evident that all these "human" traits started evolving millions of years before the first human descended from the trees to take his first tentative steps in the African savannah.
Now, Dr. Ajit Varki, a University of California, San Diego, glycobiologist, is trying to uncover the mystery of human uniqueness.[1] Glycobiology is the study of sugars, and especially oligo- and polysaccharides, in biology.
In humans the most common polysaccharide that coats the cell surface is a type of sialic acid called N-acetyl neuraminic acid. But Dr Varki discovered that we are the only animal that has this molecule exclusively. All other animals have a different sialic acid on their cell surface, called N-glycolyl neuraminic acid [Figure].

Figure. The difference between Neu5Ac and Neu5Gc: 1 oxygen atom (in green).
Dr. Varki found that a mutation in an enzyme that inserts an oxygen atom into N-acetyl neuraminic acid to make N-glycolyl neuraminic acid underwent a mutation in one of our prehuman forebears rendering it inactive, and that's how we humans ended up with N-acetyl neuraminic acid.[2]
Why did this mutation survive?
Dr. Varki offers a tantalizing clue. Plasmodium reichenowi,a malaria parasite that afflicts apes and monkeys, attaches itself to the cell surface by binding to N-glycolyl neuraminic acid, which humans don't have. So a single mutation allowed us to escape from at least 1 devastating disease, and maybe more. This is an enormous selective advantage.
So there you have it: one tiny difference in a single molecule, and what momentous consequences it has wrought.
I am Dr. Dov Michaeli of http://www.thedoctorweighsin.com/
References
- Lieberman B. Human evolution: details of being human. Nature. 2008;454:21-23. Abstract
- Chou HH, Takematsu H, Diaz S, et al. A mutation in human CMP-sialic acid hydroxylase occurred after the Homo-Pan divergence. Proc Natl Acad Sci U S A. 1998;95:11751-11756. Abstract
By Medscape:
Readers are encouraged to respond to the author at michaelid@comcast.net or to Peter Yellowlees, MD, Deputy Editor of The Medscape Journal of Medicine, for the editor's eyes only or for possible publication as an actual Letter in the Medscape Journal via email: peter.yellowlees@ucdmc.ucdavis.edu
Sunday, 14 June 2009
Did You Know: Pandemic Phases of Influenza
This is taken off of the WHO site, there's a link at the end of the post for a full detail.
This blog post has only the meaning of each phase.
Phase 1: No animal virus that could cause influenza among humans
Phase 2: Virus circulating among wild and domesticated animals. Known to infect humans and possible pandemic threat.
Phase 3: An animal or human-animal influenza that has caused sporadic cases. No human to human transmission.
Phase 4: Human to human transmission of the virus that can cause a community level outbreak
Phase 5: Community level outbreaks in two countries and one WHO region.
Phase 6: Phase 5 + community level outbreak in one other country of another WHO region
Post Peak Period: Level of pandemic influenza has dropped below peak levels, when under surveillance
Post Pandemic Period: Level of influenza has returned to that of the peak of seasonal influenza in most countries when under surveillance
H1N1 influenza has reached phase 6 pandemic.
Link: http://www.who.int/csr/disease/influenza/GIPA3AideMemoire.pdf
Thursday, 14 May 2009
Venous Return
Did you know: Why prop patient's leg upwards for First Aid (14th May 2009)
After witnessing a trauma with no emergency backup within 15 minutes, all persons are trained to assess the situation firstly and follow the shock treatment protocol.
One of these steps involve placing the patients leg on a pillow 8-10 inches above the level of the head.
Why?
To increase the venous return and thereby increase cardiac output and hence maintain blood flow to the brain and other vital organs.
During hemorrhagic shock, blood volume decreases and so the venous return decreases. After stopping blood leak, the next step is to supply enough blood to the heart to pump.
Did You Know: What happens physiologically when you pick up a large object? (14th May 2009)
What happens physiologically when you are picking up a really large object or are trying to relieve yourself of constipation?
((Warning: if you're not a med student or someone who has studied physiology before, this may sound confusing/weird))
To make it easy I'll take the example of lifting a really large object:
Whilst carrying a really large object and forcing expiration against your glottis you are performing the Valsalva maneuver.
The intrathoracic pressure becomes positive due to compression of the thoracic organs by the contracting rib cage.
This intrathoracic pressure increase compresses the vessels and cardiac chambers.
Veins are compressed and the right atrial pressure increases majorly causing the venous return to decrease.
This reduced venous return, and along with compression of the heart, reduces the cardiac filling.
Reduced filling causes a fall in cardiac output according to the Frank Starling's Law.
And by default a decreased blood pressure.
The compression of the thoracic aorta causes the aortic pressure to increase, initially.
But then the aortic pressure begins to fall after a few seconds because cardiac output is decreasing.
(Heart rate is regulated by the increasing or decreasing blood pressure)
Due to the baroreceptor reflex, the heart rate decreases because aortic pressure is elevated and then the heart rate increases as the aortic pressure falls.
When the person starts to breathe normally again, aortic pressure briefly decreases as the pressure on the aorta is removed, and heart rate briefly increases.
Due to the rapid increase in cardiac filling the cardiac output increases and the aortic pressure increases simultaneously causing the heart rate to decrease again.
Therefore due to the baroreceptors, the Aortic pressure rises above normal {Which was low due to the Valsalva maneuver} and heart rate is brought down low or normal
I know it's confusing... read it only when you have nothing else haunting you.
Sunday, 10 May 2009
Influenza A H1N1, an almost pandemic. What you need to know!
What:
Symptoms for clinical differentiation:
Prescribed treatment:
Zanamivir and Oseltamivir
Stay home (at least for a week)
Sneeze into a cloth/sleeve to avoid spread
Latest outbreak first reported: March 18 2009
Debatable concern:
Production of the Influenza A H1N1 vaccination is reducing the vaccination production for seasonal flu.
Swine flu may have aggravated other overlying diseases. Mortality cases in Mexico solely due to Swine Flu not confirmed.
Resource: Medscape
- A contagious respiratory disease originally among pigs and now among humans through direct contact/ person to person transmission and touch.
- The virus involved is traced back to the Spanish pandemic in 1918.
- WHO deemed H1N1 outbreak as stage 5. (It is one step behind from becoming a world wide pandemic)
- 109 cases reported in the USA.
Symptoms for clinical differentiation:
- Rhinorrhea
- Sore throat
- Cough
- Fever above 100 deg F
Prescribed treatment:
Zanamivir and Oseltamivir
Stay home (at least for a week)
Sneeze into a cloth/sleeve to avoid spread
Latest outbreak first reported: March 18 2009
Debatable concern:
Production of the Influenza A H1N1 vaccination is reducing the vaccination production for seasonal flu.
Swine flu may have aggravated other overlying diseases. Mortality cases in Mexico solely due to Swine Flu not confirmed.
Resource: Medscape
Thursday, 23 April 2009
King George III I don't blame you...
King George III of the United Kingdom is well known for his bouts of hysteria and porphyria.
What's porphyria?
Porphyrias are inborn errors of metabolism. They are characterized by the increase or elevation of Amino Levulinic Acid or Porphyrins. (Look down for a brief pathway of Heme synthesis).
There are many types of porphyrias but I will explain just what King George III had.
He had what is called Acute Intermittent Porphyria.
It is an inherited condition with the enzyme Uroporphyrinogen - 1 - synthase (Porphobilinogen deaminase) deficient.
Since PBG deaminase catalyses the conversion of Porphobilinogen to Hydroxymethylbilane, there's an increase in porphobilinogen and a secondary increase of ALA synthase's (Amino Levulinic Acid) activity and hence ALA and PBG increases in quantity.
Now, when ALA and PBG both increase they tend to be elevated in the urine too but they're colourless so it doesn't show in the urine UNTIL it is left to be oxidized and it turns into a coloured urine.
ALA and PBG elevation can cause neuropsychiatric symptoms whilst increase in porphyrins can cause cutaneous photosensitivity.
In AIP, ALA and PBG is elevated and it explains the bouts of madness presented by King George III. Although the rest of the symptoms are quite different in their manifestations.
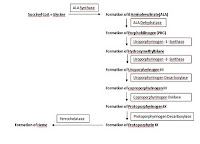
What's porphyria?
Porphyrias are inborn errors of metabolism. They are characterized by the increase or elevation of Amino Levulinic Acid or Porphyrins. (Look down for a brief pathway of Heme synthesis).
There are many types of porphyrias but I will explain just what King George III had.
He had what is called Acute Intermittent Porphyria.
It is an inherited condition with the enzyme Uroporphyrinogen - 1 - synthase (Porphobilinogen deaminase) deficient.
Since PBG deaminase catalyses the conversion of Porphobilinogen to Hydroxymethylbilane, there's an increase in porphobilinogen and a secondary increase of ALA synthase's (Amino Levulinic Acid) activity and hence ALA and PBG increases in quantity.
Now, when ALA and PBG both increase they tend to be elevated in the urine too but they're colourless so it doesn't show in the urine UNTIL it is left to be oxidized and it turns into a coloured urine.
ALA and PBG elevation can cause neuropsychiatric symptoms whilst increase in porphyrins can cause cutaneous photosensitivity.
In AIP, ALA and PBG is elevated and it explains the bouts of madness presented by King George III. Although the rest of the symptoms are quite different in their manifestations.

Wednesday, 1 April 2009
Did you know: Hurler's Syndrome and Pseudo-Hurler's syndrome (1st April 2009)
Hurler's Syndrome:
It is an autosomal recessive catabolism disorder of the proteoglycans. Hydrolases that break the glycosaminoglycans present in the proteoglycans structures, inside the lysosomes are deficient. Due to this, products like dermatan sulphate and heparan sulphate accumulates in the lysosomes instead of being excreted in the urine.
Mental Retardation and mesenchymal defects are seen in the patient.
Pseudo-Hurler's syndrome:
It is due to the reduced availability of GlcNAc phosphtransferase that converts mannose to mannose-6-phosphate that is targeted to the lysosomes. Instead due to the fact that they are not converted they are sent out of the cell.
Psychomotor retardation and skeletal deformities are prominent.
Tuesday, 17 March 2009
Neuroanatomy Links
Like last time, I'm going to post the links that I found extremely useful during my neurobiology course and some which I wished I would have seen it earlier to the final exam day.
I thought neurobiology would be disastrous but ho ho ho... I am hell happy with the it. Best of luck.
There you go... I know its not in order but I really don't have the time :D
Erm' remember to do alot of practice cases... the only way to learn is to know that you don't know something :D
Cheerz!!
I thought neurobiology would be disastrous but ho ho ho... I am hell happy with the it. Best of luck.
- http://neuroscienceupdate.cumc.columbia.edu/popups/transcript_carmel.html
- http://www.med.harvard.edu/AANLIB/home.html (ATLAS)
- http://download.videohelp.com/vitualis/med/brainstem_1.htm
- http://www.yorku.ca/eye/toc.htm (Visual related topics)
- http://www.uwm.edu/~johnchay/sb.htm (Split brain syndrome)
- http://www.sonoma.edu/users/h/hanesda/B497/bear11.htm (Auditory and vestibular system)
- http://neuroscience.uth.tmc.edu/index.htm (Neurophysiology... absolutely brilliant site)
- http://www.utoronto.ca/neuronotes/NeuroExam/cranial_5b.htm (Quick review of all cranial nerves)
- http://www.neuroexam.com/content.php?p=27 (Examination of the cranial nerves)
- http://www.neuroanatomy.wisc.edu/virtualbrain/BrainStem/14CNVII.html (MUST READ WEBSITE! I wish I had seen this earlier)
- http://www.anatomy.dal.ca/Human_Neuroanatomy/Labs/LabExercises.html
- http://www.yorku.ca/eye/eyemove.htm (Eye movements)
- http://books.google.com/books?id=U5sPAN53fjoC&pg=PA51&lpg=PA51&dq=function+of+protoplasmic+astrocyte&source=bl&ots=iXMN2YWAfr&sig=vsM7Ch8TVc08_Ri-YXFU9B9JUkE (Histology of CNS/PNS)
- http://www.neurophys.wisc.edu/h%26b/textbook/chap-7.html (Vestibular apparatus)
- http://www.csuchico.edu/~pmccaffrey/syllabi/CMSD%20320/362unit4.html (Cerebral cortex/lobes/Broadmann's Areas)
- http://brainmaps.org/index.php?action=viewslides&datid=17 (MRI Heaven!!)
- http://emedicine.medscape.com/neurosurgery
- http://wiki.cns.org/wiki/index.php/Main_Page (Neuro Wikipedia?!? Amazing site)
- http://books.google.com/books?id=trFI0pzT-DIC&pg=PA175&lpg=PA175&dq=unsteadiness+when+eyes+are+open&source=web&ots=6iL_huvxD1&sig=OH3WIg6MtZXU7h6OkPYM5dMytU8&hl=en&sa=X&oi=book_result&resnum=3&ct=result#PPA175,M1 ((Disorders of the CNS...))
- http://books.google.com/books?id=k8qv-6tqZL0C&pg=PA65&lpg=PA65&dq=UMN+lesion+of+corticobulbar+tract&source=bl&ots=_mWmsf-Msh&sig=qG2NfweDqnQJIeT3l0WzvD6i9xQ&hl=en&ei=XjeMSf2lO5icNeXUma4L&sa=X&oi=book_result&resnum=6&ct=result#PPA68,M1
There you go... I know its not in order but I really don't have the time :D
Erm' remember to do alot of practice cases... the only way to learn is to know that you don't know something :D
Cheerz!!
Monday, 5 January 2009
The 'to-go' links
Here are some links that I used during my anatomy course. Use it well. I have arranged them according to my bookmark so they might come off as disorganised, sorry about that. Most of the links are specific pages, do scroll up or down to get to the home page for further reference.
Any doubts, do message back. Till then study well and best of luck.
- Tables of all muscles, nerves, arteries, veins etc.: http://anatomy.uams.edu/AnatomyHTML/medcharts.html
- http://anatomy.med.umich.edu/
- http://anatomy.med.umich.edu/courseinfo/module_index.html
- Muscles of the hand: http://home.comcast.net/~wnor/lesson5mus%26tendonsofhand.htm
- Course of the ulnar nerve: http://depts.washington.edu/anesth/regional/Page1.html
- Brilliant modulator of muscles: http://www.getbodysmart.com/ap/muscularsystem/armmuscles/menu/menu.html
- British Medical Journal: http://student.bmj.com/
- http://www.anatomy.wisc.edu/courses/gross/
- Embryology: http://www.embryology.ch/anglais/sdigestive/leber03.html
- Embryology: http://books.google.com/books?id=WbCsJTWlAgUC&pg=PA129&lpg=PA129&dq=condition+of+lungs+of+a+stillborn+infant&source=web&ots=wgq3EaqgQJ&sig=ppzc-lnz6o3C8sKJq1rutQHYPgU#PPA107,M1
- Forearm muscles: http://www.gwc.maricopa.edu/class/bio201/muscle/arm/frma.htm
- http://download.videohelp.com/vitualis/med/mmforarm.htm
- Gray's Anatomy: http://www.bartleby.com/107/
- Hand: http://eatonhand.com/hom/hom033.htm
- Femoral Triangle or adductor canal: http://www.gla.ac.uk/ibls/US/fab/tutorial/anatomy/femoralt.html
- Anatomy notes: http://anatomynotes.blogspot.com/
- Upper Limb movements: http://anatomy.med.umich.edu/modules/upper_limb_module/upper_limb_05.html
- Practice questions for Lower limb: http://anatomy.med.umich.edu/musculoskeletal_system/leg_questions.html
- Practice questions for Upper Limb: ttp://www.aippg.net/forum/viewtopic.php?t=6213
- Heart: http://images.google.com/imgres?imgurl=http://cr-anatomy-notes.com/Images/image006.jpg&imgrefurl=http://cr-anatomy-notes.com/Heart.aspx&usg=__Jr4aJ7698wEz-8Gfh5nHfr2-jUs=&h=559&w=629&sz=50&hl=en&start=5&um=1&tbnid=kwR2bRqO-zEF1M:&tbnh=122&tbnw=137&prev=/images%3Fq%3Dpulmonary%2Bartery%26um%3D1%26hl%3Den%26sa%3DN
- Inguinal region: http://download.videohelp.com/vitualis/med/inguinal_region.htm
- Inguinal hernia: http://www.sh.lsuhsc.edu/gallery/tools/inguinal/testis16.swf
Any doubts, do message back. Till then study well and best of luck.
Wednesday, 8 October 2008
The medical speciality test
I know its a bit too earlyto be even thinking about speciality right now. I'm just in my 4th year. But oh well, I want to know after 2 year how I would probably change. So, here goes.
Link: http://www.med-ed.virginia.edu/specialties/
Results:
Rank
Specialty
Score
1
occupational med
48
2
otolaryngology
48
3
orthopaedic surgery
48
4
rheumatology
48
5
radiation oncology
48
6
pulmonology
47
7
endocrinology
47
8
cardiology
47
9
dermatology
47
10
ophthalmology
47
11
pathology
47
12
colon & rectal surgery
46
13
anesthesiology
46
14
neurosurgery
46
15
med oncology
46
16
hematology
45
17
neurology
45
18
plastic surgery
45
19
urology
45
20
thoracic surgery
44
21
radiology
44
22
gastroenterology
44
23
emergency med
44
24
infectious disease
44
25
nephrology
44
26
allergy & immunology
43
27
physical med & rehabilitation
43
28
preventive med
43
29
nuclear med
42
30
general surgery
42
31
pediatrics
41
32
psychiatry
40
33
obstetrics/gynecology
40
34
aerospace med
39
35
general internal med
38
36
family practice
36
Now, what I am most glad is that this test litreally confirms my resistance towards OB/GYN and PEDs.
Its a 130 questions. They're intentionally repeated... don't lie on the test. You'd really come to know about what you're probably capable of.
My results... the first 10 are the ones that I basically don't like so much except orthopedic surgery. That might be fun... after all how many women do you know are actually in ortho surgery?
Cheerz
Thursday, 14 August 2008
Presentation pointer
Ben Ferguson of the University of Chicago shared on the Medscape blog a few pointers about what to do and not to do at a presentation. It is very helpful and although I knew some of the pointers I just thought it was brilliant.
This is a short paragraph of the blog entry. Please click the link below it to read the whole thing.
Ben Ferguson -- I’m currently at a conference on worms (don’t ask), struggling to stay awake through 22(!) rapid-fire presentations each day. Some are average, some are really quite good, and some are just annoying and terrible.
This is a short paragraph of the blog entry. Please click the link below it to read the whole thing.
How Not to Give a Presentation
Ben Ferguson -- I’m currently at a conference on worms (don’t ask), struggling to stay awake through 22(!) rapid-fire presentations each day. Some are average, some are really quite good, and some are just annoying and terrible.
We all know the typical no-nos -- don’t talk too quickly, don’t put too many words on one slide, don’t read directly from your slides, don’t make the text too small to be legible, don’t be rigid but don’t move around too much either. So many don’ts.
Even if you didn’t think it was possible, I have more. It’s weird, but people always forget how to do the most basic things when they’re in front of a large audience. If you can help it, don’t do this either. Some pointers for your own future presentations:
• Don’t mistake the wireless slide changer for the laser pointer. If you absolutely must, at least recognize this within the first few slides, and try not to use the slide changer as the laser pointer for your entire presentation or until an annoyed audience member interrupts you to inform you that you are not, in fact, actually pointing to anything. ...
http://medscape.typepad.com/thedifferential/2008/08/how-not-to-give.html?cid=126309766#comment-126309766
Subscribe to:
Posts (Atom)